

Written by Dr Wolfgang Muller
Written 01/07/2021 – Last major review 01/05/2025 – Last minor review –/–/—- – Next mandatory review by Nov 2026
Click on subject in CONTENT to go straight there and click on subject in the TEXT to go back to CONTENT
Content
My child is always sick – this cannot be normal!
How many infections may be completely normal in children over one year?
Why does my child seem to be so different to other children?
Why is it normal that children between the age of 6 months and 5 years have so many infections?
If this is all normal then surely I do not have to worry at all?
What is the minimum workup my child should have if I am worried about frequent infections?
What can I do to make my child better?
What could be wrong with my child to make him/her get so many infections?
Overview of conditions contributing to recurrent infections
Environmental factors
Fluid Aspiration
Abnormalities of the lungs
Nutritional deficiencies
Recurrent viral induced wheeze and airborne triggers
Deficiencies of the immune system
Temporary lung conditions
Chronic lung conditions
“Is it normal for my child to be sick this often?”
There is hardly a week that goes by without me being asked this question—whether in clinic or in the Emergency Department. Parents are understandably concerned when their infant or toddler seems to be catching one infection after another.
It can feel as though no month passes without a fever, a lingering cough, or yet another episode of illness. The most common complaints include a persistent cough that just won’t go away, fevers that return like clockwork, or a constantly runny nose. Some children frequently complain of a sore throat, while others seem generally unwell more often than not.
Naturally, parents wonder: “Surely this can’t be normal—how could it be?”
To answer that question, we first need to understand: What is normal when it comes to childhood infections?

Well, first of all, it depends on the age of the child!
The age group I most commonly see with recurrent infections is between 8 months and 5 years. While the first infections often begin around 6 months of age, most children are around 8 months old by the time the pattern of “recurrent” infections becomes noticeable.
It’s not unusual for some infants to experience bronchiolitis even earlier—sometimes from as young as 4 to 6 weeks.
If your child falls outside this age range, I would recommend seeing a doctor for a more detailed assessment, as further investigation may be necessary.
Between 6 months and 5 years, a child’s immune system is still developing, and responses to viral or bacterial exposures can vary significantly from one child to another.
How much coughing and how many infections are “normal”?
Studies from London and other parts of the world have shown that even healthy children—without any infections—may cough up to 11 times a day on average. That said, this can vary significantly, ranging from as few as 1 to as many as 34 coughs per day in otherwise well children¹.
Other research has looked into how many respiratory infections occur in healthy children each year. On average, children experience 3 to 6 infections annually, though in some children (with no underlying medical conditions), the number can be as high as 12 infections per year² ³ ⁴.
One of the most frequent questions parents ask is:
“How long should a cough last?”
This is a difficult question to answer definitively because it varies greatly depending on the child and the nature of the infection. As discussed under “Acute Viral Illness – What Can I Do?”, studies suggest that most coughs resolve within 1 to 3 weeks⁵.
A group of Australian researchers found that:
50% of children had stopped coughing by day 10
90% of children had stopped by day 25
However, about 8% of children continued to cough beyond 28 days⁶, which may still be within the expected range for recovery from certain viral infections.
Some children may go on to develop what is known as a habit cough, which is discussed in more detail under “Respiratory – Habit Cough.”
“I often show this picture to parents to illustrate how many days in a year a perfectly healthy child could be unwell—marked in red—if they experience 12 infections, each lasting around three weeks.”
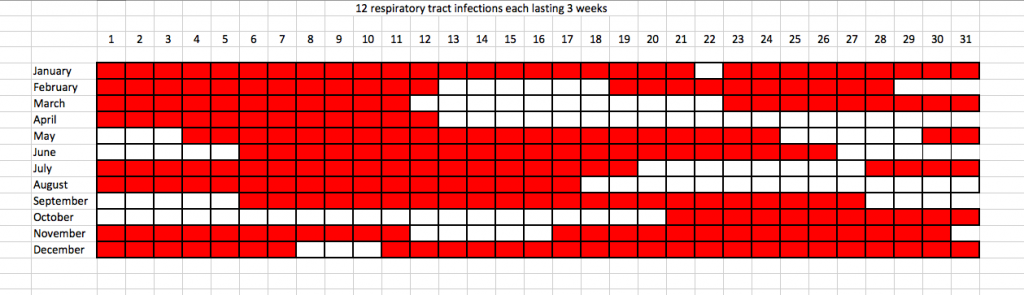
During the peak of the season it is not unusual to go from one infection straight into the next. This may be with a period of slight improvement before they are getting worse again or not even with any improvement in-between.
- Munyard, P. & Bush, A. How much coughing is normal? Arch. Dis. Child. 74, 531–534 (1996).
- Grüber, C. et al. History of respiratory infections in the first 12 yr among children from a birth cohort. Pediatr. Allergy Immunol. Off. Publ. Eur. Soc. Pediatr. Allergy Immunol. 19, 505–512 (2008).
- von Linstow, M.-L. et al. Acute respiratory symptoms and general illness during the first year of life: a population-based birth cohort study. Pediatr. Pulmonol. 43, 584–593 (2008).
- Bryant, P. A. & South, M. Fifteen-minute consultation: The infant with frequent infections. Arch. Dis. Child. Educ. Pract. Ed. 99, 8–12 (2014)
- Hay, A. D., Wilson, A., Fahey, T. & Peters, T. J. The duration of acute cough in pre-school children presenting to primary care: a prospective cohort study. Fam. Pract. 20, 696–705 (2003).
- Hay, A. D. & Wilson, A. D. The natural history of acute cough in children aged 0 to 4 years in primary care: a systematic review. Br. J. Gen. Pract. J. R. Coll. Gen. Pract. 52, 401–409 (2002).

Why are not all children the same?
This is actually one of the easier questions to answer—because we know that no two children are ever exactly alike, not even twins.
Some children are taller, some shorter; some are naturally athletic, musically gifted or artistic, while others may shine in maths or language. Just as children vary in their physical and cognitive development, the same is true for their immune systems.
In some children, the immune system builds up its defences with very few visible symptoms. In others, it reacts more noticeably, with frequent fevers, coughs, or other signs of infection. This variation isn’t unique to children—it’s something we see in adults as well. In medicine, it’s long been recognised that some people show hardly any symptoms when they have an infection, while others may feel very unwell before recovering.
There are many factors that influence this, but one important reason is that our immune systems respond differentlyfrom person to person.
So yes, I regularly see significant variation—even within the same family. It’s not uncommon for one sibling to be frequently unwell while the other remains largely unaffected, and this can even be true in twins.
It’s really not so different from one child being taller or more energetic than another.
…But most importantly:
your child is most likely not so different from many other children—you just may not have encountered it in your circle until now.
Could something be missed?
Most of us have heard stories of conditions that went undiagnosed for many months—or even longer—before finally being recognised. In some cases, the delay can make treatment more difficult or less effective. This is why I strongly recommend a careful clinical review, as it is key to reducing the risk of missing something important.
In the majority of cases, a thorough history and physical examination—without the need for extensive testing—provides all the information I need to form a clear clinical impression.
I’ve covered related topics in more detail elsewhere, including:
While every case is unique, it’s also important to remember:
If your child is growing and developing normally overall, there is usually time to explore carefully whether anything is truly wrong or not.
Why do babies and young children get so many infections?
This is largely because their immune system has not yet fully developed.
At birth, newborns receive a helpful “head start” in the form of passive immunity from their mother. While still in the womb, babies are given immunoglobulin G (IgG)—antibodies that cross the placenta and provide protection, mainly against viral infections. After birth, breastfed infants also receive immunoglobulin A (IgA) from breast milk, which offers additional protection—particularly against viral infections of the gastrointestinal tract.
However, this early immunity has limitations. It offers less protection against bacterial infections, which is why we are particularly cautious when a young infant (especially under 3–6 months) develops a fever. These babies are often thoroughly assessed to rule out serious bacterial illness.
While the passive immunity to viral infections can be quite effective, it begins to decline around 5–6 months of age, and from that point onward, viral infections become increasingly common.
From then on, babies are essentially “on their own”—they must build their own immunity by being exposed to and fighting off infections. This process is most active and noticeable in the early years up to school age, but in reality, immunity-building is a lifelong process.
I sometimes explain this to parents using a simple analogy:
Imagine a young person who receives a one-time “pocket money” gift from their parents before heading out into the world. That money helps them get started, but eventually it runs out—and they then have to earn their own income. Similarly, passive immunity protects babies for a while, but once it fades (around 6 months), they must start building their own defences. There may be a challenging period of frequent infections—“low funds,” so to speak—until their immune system becomes stronger and more independent.
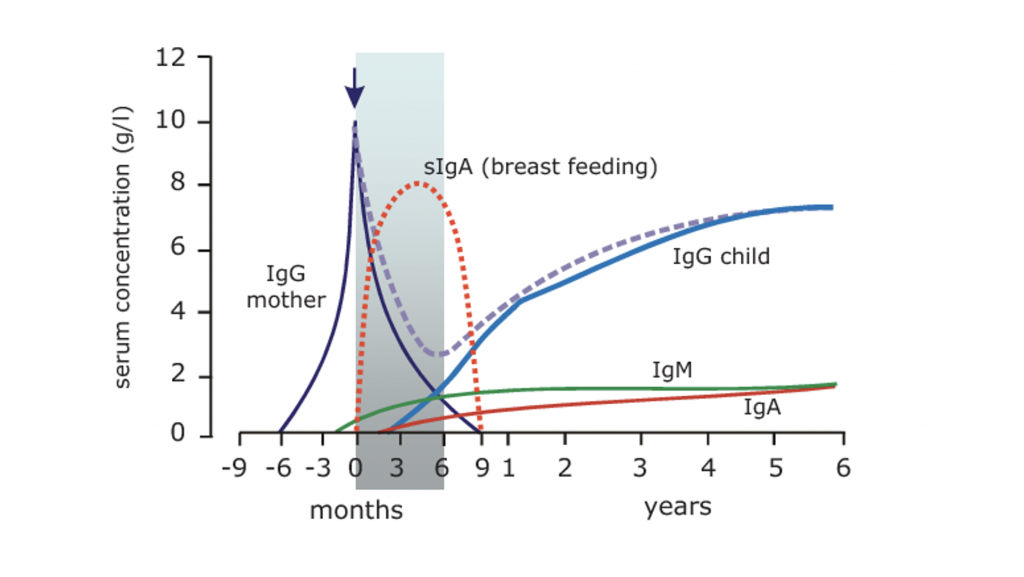
Understanding Your Child’s Immune Protection: Why Babies Get Sick So Often
The graph nearby may look complex, but it illustrates a key concept: the natural protection babies receive from their mothers before birth (known as IgG) starts to decline soon after they are born. This leaves infants gradually more exposed to infections until their own immune system matures.
What Are Immunoglobulins?
Immunoglobulins—often referred to as antibodies—are proteins the body produces to help defend against infections. There are several types, but the most important ones in early life are:
IgG – Passed from mother to baby through the placenta before birth; helps fight infections the mother has previously encountered
IgA – Found in breast milk and helps protect the surfaces of the lungs, gut, and throat
IgM – The first antibody the body produces when encountering a new infection
IgE – Usually involved in allergic reactions (less relevant to early infection defence)
How Immunity Works in Babies: A Simple Analogy
Think of immunoglobulins as a police force protecting the body:
IgM is like the first responders—they arrive quickly when something unfamiliar enters the body (like a new virus). However, they take a few days to gear up.
IgG is the experienced detective—they remember past intruders and call in IgM reinforcements faster if the same bug shows up again.
IgA patrols the outer borders—the lungs, gut, and other entry points, helping to keep germs from getting in at all.
What Happens After Birth?
While still in the womb, babies receive a generous supply of IgG from their mother.
After birth, this supply gradually fades—there is no more IgG passed on after delivery.
If breastfed, babies also receive IgA from breast milk, which helps protect the respiratory and digestive tracts.
However, around 3 months of age, a baby begins making their own IgM, IgG, and IgA, but this process is slow. The gap in immunity is most noticeable between 5–9 months, when maternal antibodies are fading and the baby’s own defences are still developing.
This is why 6 months to preschool age is a time when frequent infections are very common.
Why Does My Child Keep Getting Sick?
This is part of normal immune development. As children grow and come into contact with viruses—especially from other children—they gradually build their own immune memory. Each time they get sick, their immune system gets stronger.
It’s also important to know that some infections can be spread by people who don’t have symptoms. This means your child may still catch viruses even at home, not just in nursery or school.
If you’re concerned about how often your child is sick, remember:
Most children do recover well.
If your child is growing, developing, and thriving, there is usually no reason to worry.
But a clinical review can provide reassurance and rule out any rare underlying problems.
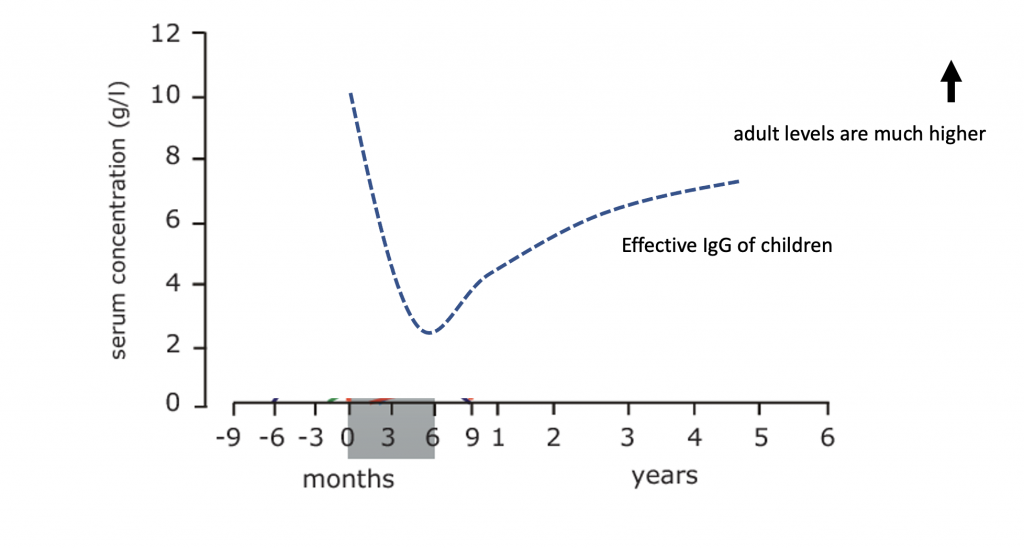
What Does a Child’s Immune Protection Really Look Like?
The graph you’ve just seen shows the combined levels of immunoglobulins in a young child over the first five years of life. These represent the body’s natural defence against infections.
As illustrated, the total immune protection a child has in early life is significantly lower than that of an adult. This is why it is completely normal for young children—especially those under five—to experience frequent infections such as colds, coughs, and fevers.
Building Immunity Over Time
Throughout our lives, every infection we overcome contributes to building our immune system. While we may naturally lose some immunoglobulins over time, the immune “memory” we build—especially in childhood—creates long-term resilience.
A Key Concept for Lifelong Health
Here’s something important to consider:
The stronger and more diverse our immune system becomes in childhood, the better protected we are in later life.
This means that exposure to common childhood infections may actually help reduce the risk of complications from illness in old age, such as secondary pneumonia after a cold.
In short:
The more infections we fight in childhood,
The stronger our immune foundation becomes,
And potentially, the longer and healthier our lives may be.
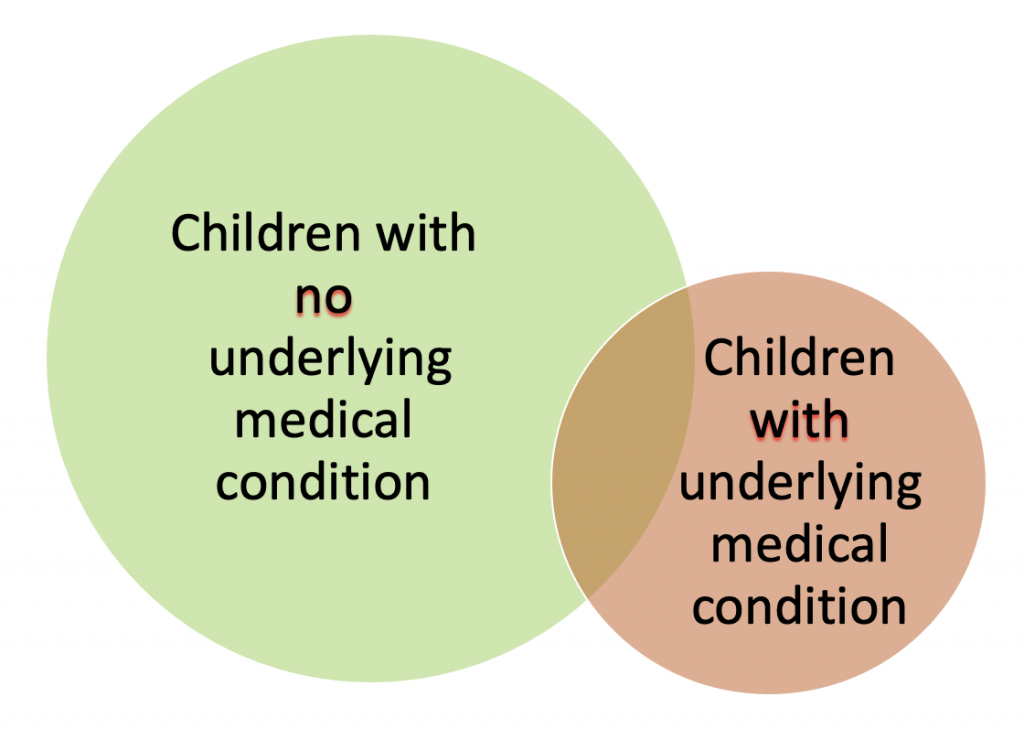
It’s Not Always Black and White
When it comes to children’s health, life is rarely straightforward. Things are not always “black or white” or simply “right or wrong.”
For example, if we say that 95% of healthy children can have up to 12 infections per year, each lasting up to three weeks, that still leaves 5% of healthy children who may experience even more infections—and still be entirely well overall.
Conversely, a child who does have an underlying medical issue may not necessarily have 12 infections a year. They could have fewer, but those infections may behave differently—becoming more severe, harder to treat, or lasting longer than expected.
This illustrates an important point:
There is an overlap between children who are perfectly healthy but frequently ill, and children who do have something medically concerning going on—but present in a similar way.
What Should You Do as a Parent?
Because of this overlap, it’s important that children with frequent infections are seen by a doctor.
A careful clinical assessment can help determine:
Whether your child’s infections fall within the expected range, or
Whether further investigation or specialist input might be needed.
In many cases, it’s simply a matter of watchful waiting, reassurance, and ongoing support. But sometimes, early identification of something more serious can make all the difference.
If your child is experiencing frequent infections, they should be seen in person by a doctor for a detailed medical history and a thorough physical examination.
In my experience, 70–90% of children seen for frequent infections do not require any further investigations after careful clinical assessment.
However, if your doctor decides that no tests are needed at the time, it is important that they also recommend a period of observation and offer a follow-up review—either the next time your child becomes unwell, or within 3 to 6 months, whichever comes first.
This approach ensures that any potential concerns are not missed and that your child’s progress can be monitored appropriately over time.
There are many supportive measures that can help your child feel better when they are suffering from a viral infection. While no remedy offers an instant cure, these approaches can relieve symptoms, support recovery, and even boost the immune system when it’s under strain.
I’ve outlined these helpful remedies in more detail in a separate section:
It is not possible to explain every possible condition in plain English here on this website but I will list most of those I usually exclude with history plus examination and/or further tests:
1) Environmental factors
2) Fluid Aspiration
3) Abnormalities of the lungs
4) Nutritional deficiencies
5) Recurrent viral wheezing and airborne triggers
6) Deficiencies of the immune system
7) Temporary lung conditions
8) Chronic lung conditions
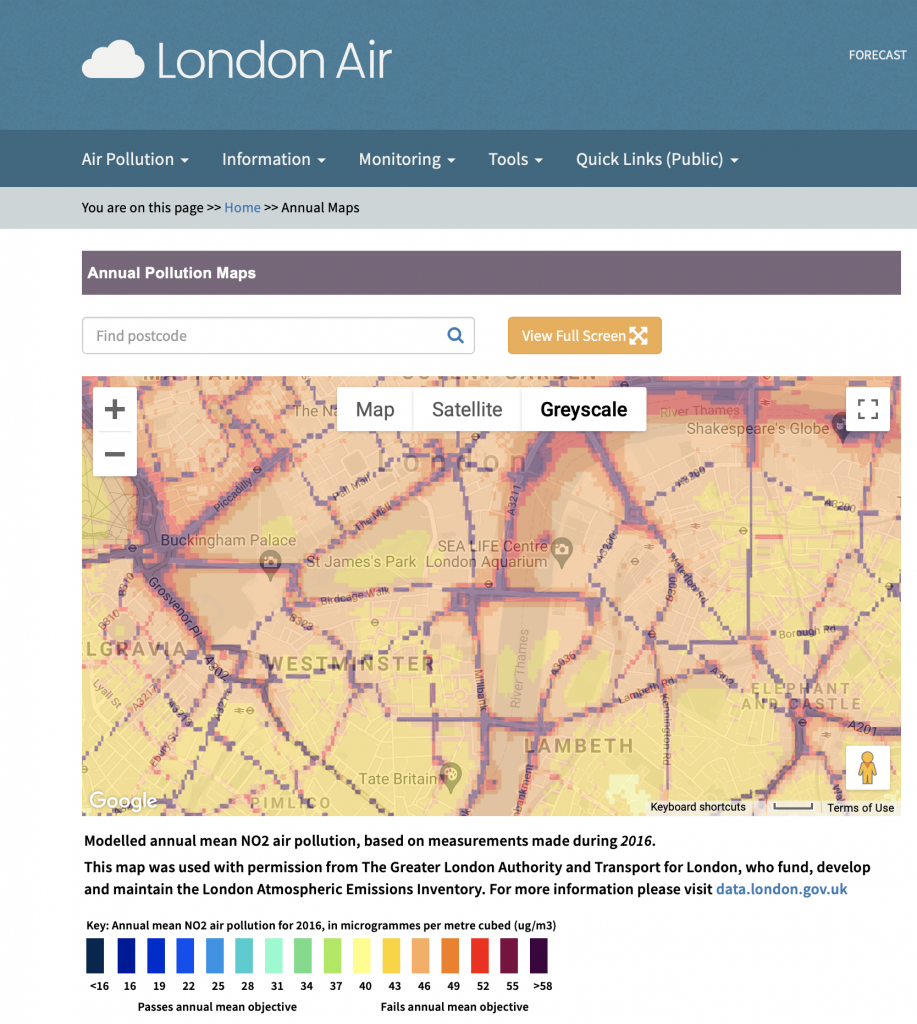
Air Quality and Your Child’s Health
Air quality is increasingly recognised as a major contributing factor to both acute and chronic respiratory illnesses, particularly in children.
You can monitor local air pollution levels using resources such as London Air , which provides real-time updates for your area—including places your child may be exposed, such as on the way to school or the shops.
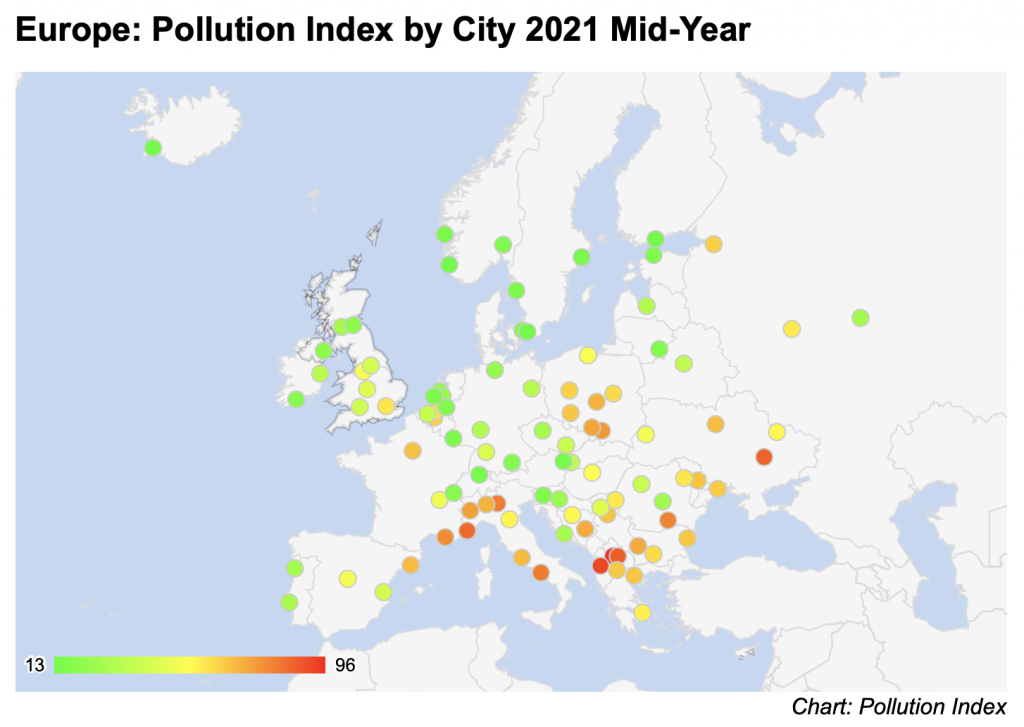
For a broader perspective, including how London’s air quality compares to other cities across Europe and worldwide, you can visit www.numbeo.com.
Smoking, Vaping, and Children’s Lung Health
What continues to surprise me—even after many years of caring for children with chronic coughs and respiratory concerns—is how often smoking or vaping is dismissed as a contributing factor by parents.
Active and passive smoking are among the best-researched and most clearly established risk factors for recurrent and chronic lung problems in children. Yet one of the most common responses I hear is:
“Yes, I do smoke—but only outside.”
“It’s just vaping.”
It’s important to understand that even smoking outdoors does not eliminate exposure, especially if clothes, hair, or nearby environments carry residual smoke particles. Similarly, the long-term effects of vaping are still being studied, but current evidence suggests it is not risk-free, particularly for developing lungs.
In addition to the direct effects of second-hand smoke, parental smoking is one of the strongest predictors of whether a child will take up smoking during adolescence. (7)
Support Over Blame
While it can be easy to place blame on a family member who smokes, it’s much harder—and far more important—to offer real support in helping someone quit. Smoking cessation is challenging, but it’s one of the most impactful health decisions a person can make—not just for themselves, but for their entire family.
I’ve included links to trusted smoking cessation programmes on my website, and I encourage families to approach quitting as a united effort. Every bit of support helps, and the benefits—especially for your child’s lung health—are truly significant.
7. Vuolo, M. & Staff, J. Parent and child cigarette use: a longitudinal, multigenerational study. Pediatrics 132, e568-577 (2013).

Other environmental factors such as mould, pet allergens and house dust are covered under allergic conditions.
Pulmonary Aspiration of Liquids
Chronic aspiration of liquids (such as drinks, refluxed gastric contents, or pooled oral secretions) repeatedly introduces fluid and bacteria into the lower airways of small children, overwhelming normal clearance mechanisms (mucociliary transport and cough). This causes ongoing airway irritation and inflammation, impairs local host defences, and can lead to areas of poor ventilation and mucus plugging, which provide an ideal environment for pathogens to proliferate. Over time, this cycle increases the risk of recurrent lower respiratory tract infections (including aspiration pneumonias), can produce persistent wet cough and wheeze, and may contribute to longer-term lung injury such as atelectasis or bronchiectasis if aspiration is not addressed.
Chronic aspiration in small children is diagnosed by combining a careful history (coughing, choking, “wet” voice, colour change, or increased work of breathing during or shortly after feeds; recurrent pneumonias; poor weight gain) with targeted investigations. A speech and language therapy feeding assessment is often the first step, followed by an instrumental swallow study to confirm aspiration—most commonly a videofluoroscopic swallow study (VFSS) or fibreoptic endoscopic evaluation of swallowing (FEES). Chest imaging may show suggestive patterns (recurrent infiltrates, often dependent or right-sided, atelectasis, or evolving bronchiectasis), and flexible bronchoscopy with bronchoalveolar lavage can help exclude other pathology and support aspiration (e.g., lipid-laden macrophages is non-specific; pepsin/bile acids may suggest reflux-related aspiration where available). If gastro-oesophageal reflux is suspected, pH–impedance monitoring and/or upper GI contrast studies may be used to assess reflux and anatomical contributors, alongside evaluation for underlying neuromuscular, airway, or structural causes.
Chest X-Rays and Recurrent Infections in Children
A plain chest radiograph (chest X-ray) is often the first imaging test we consider when investigating children with frequent or persistent respiratory symptoms.
There are many underlying causes of recurrent infections that can be identified—or ruled out—on a chest X-ray. These may include:
Congenital abnormalities (present from birth)
Inhaled foreign bodies (such as small food particles or toys)
Structural or rare lung conditions
In most cases, I recommend performing at least one chest X-ray, unless a recent one has already been done and reported as normal. I may ask parents or caregivers to obtain either the radiology report or the actual image, as I prefer to review the films myself rather than rely solely on a written summary.
What About Radiation Exposure?
Modern X-ray equipment uses very low doses of radiation. In fact, very few people realise that:
A 2–3 hour flight, or one extra day of background radiation from natural environmental sources, exposes a child to about the same amount of radiation as one chest X-ray.
This means the diagnostic benefit of a chest X-ray—particularly in the context of recurrent infections—greatly outweighs the minimal risk.
In my experience, nutritional deficiencies are a major contributing factor to recurrent infections in children. Many toddlers—especially during periods of fussy eating—tend to have diets that lack variety, particularly when it comes to green vegetables and other nutrient-rich foods.
In clinical practice, I frequently encounter iron and vitamin deficiencies, both of which can weaken the immune systemand reduce a child’s ability to fight infections effectively. Even when parents believe their child is eating well, it’s important to remember that growing children have high nutritional demands that can be difficult to meet through diet alone.
Multivitamin supplements are often not given, given inconsistently, or not well tolerated, and parents are sometimes surprised to realise they may be administering them less regularly than they thought.
The Good News
These deficiencies can usually be detected through simple blood tests and are relatively easy to correct. In many cases, addressing nutritional imbalances leads to noticeable improvements in:
A child’s overall health and energy
School or nursery performance
And most significantly, a reduction in the frequency and severity of infections
Some children experience recurrent wheezing or are sensitised to airborne allergens. These children may not necessarily have more infections than others, but they tend to show more severe or prolonged symptoms when they do become unwell with common colds or coughs.
As a result, the recovery time between episodes is often short, and it can appear as though they are “constantly ill”, even when no new infection is present.
There is often a family history of conditions such as:
Asthma
Hay fever (allergic rhinitis)
Eczema
Food allergies
While food allergies alone do not increase susceptibility to infections, they are often associated with other allergic conditions such as asthma and hay fever, which can influence how a child responds to viral illnesses.
In some cases, it may be helpful to screen for sensitisation to common airborne allergens, including:
Mould
House dust mites
Pet dander
Pollen (from trees, grasses, or weeds)
Identifying these triggers can guide preventive strategies and symptom management, helping to reduce the frequency and severity of respiratory symptoms.
Severe Immunodeficiencies
Understandably, many parents worry about the possibility of a serious immune system problem. However, severe immunodeficiencies typically present very differently from common childhood infections.
Children with significant immune deficiencies usually experience recurrent, serious bacterial infections such as:
Pneumonia
Meningitis
Deep skin or soft tissue infections
These infections often begin before the age of 6 months, which is earlier than most common viral illnesses.
It’s important to note that bronchiolitis, a viral infection commonly seen in infants under 6 months of age, is nottypically a sign of immune deficiency.
Mild Immunodeficiencies
Some children may have milder or more subtle immune system issues, which become apparent from around 6 to 8 months of age and often involve recurrent viral infections.
In selected cases, further testing may be recommended to check for specific, mild immunodeficiencies such as:
While these conditions are generally not dangerous, it is helpful to be aware of them. They usually do not require daily medication, but they do mean that your child’s doctor may need to be more vigilant for bacterial infections when your child becomes unwell.
Protracted Bacterial Bronchitis (PBB)
Some children who experience frequent viral infections may go on to develop a temporary condition known as “bacterial overgrowth” in the airways. This can lead to a persistent, self-perpetuating cough that typically lasts 6 weeks or longer.
This condition is called Protracted Bacterial Bronchitis (PBB).
While it can sound concerning, PBB is usually treatable and not permanent. It’s important to recognise and address it early, as the ongoing cough can significantly affect a child’s comfort and quality of life.
Some children may have an underlying chronic lung condition, though these are very rare. It is not possible to list all such conditions here, but they are typically suspected based on:
The child’s medical history
Physical examination findings
Or findings on a chest radiograph (X-ray) as part of the initial assessment
In certain cases, further specialist investigations may be required. These would be discussed and explained by your doctor based on the clinical picture.
Thanks to routine newborn screening for cystic fibrosis, it is now uncommon for this condition to go undetected. However, it remains important for doctors to consider it carefully when taking a history and during examination, particularly if symptoms are persistent or unusual. I may be necessary to do further tests for cystic fibrosis in some cases.
This information is provided by Dr W Muller and will be regularly reviewed and updated.